Ear infections and flights tend to meet at the end of a holiday. A child has been in the pool every day, a parent has a streaming cold, and the flight home is not easy to move.
Whether flying is safe depends mainly on which part of the ear is infected, and on whether the narrow passage that balances pressure behind the eardrum is still open. The number of days since the symptoms started matters much less.
Which part of the ear is infected
An outer ear infection (otitis externa, often called swimmer’s ear) affects the canal on the outside of the eardrum. It can be very sore, but the canal is open to the cabin air, so pressure changes reach it without trouble. Flying is usually possible. Keep the drops in hand luggage, and expect the ear to feel uncomfortable rather than dangerous.
A middle ear infection (otitis media) sits behind the eardrum, in a small air space that connects to the back of the nose through the Eustachian tube. That tube is what lets pressure even out when you swallow or yawn. Infection and the congestion that usually comes with it make the tube swollen and sticky, and that is where flying causes problems.
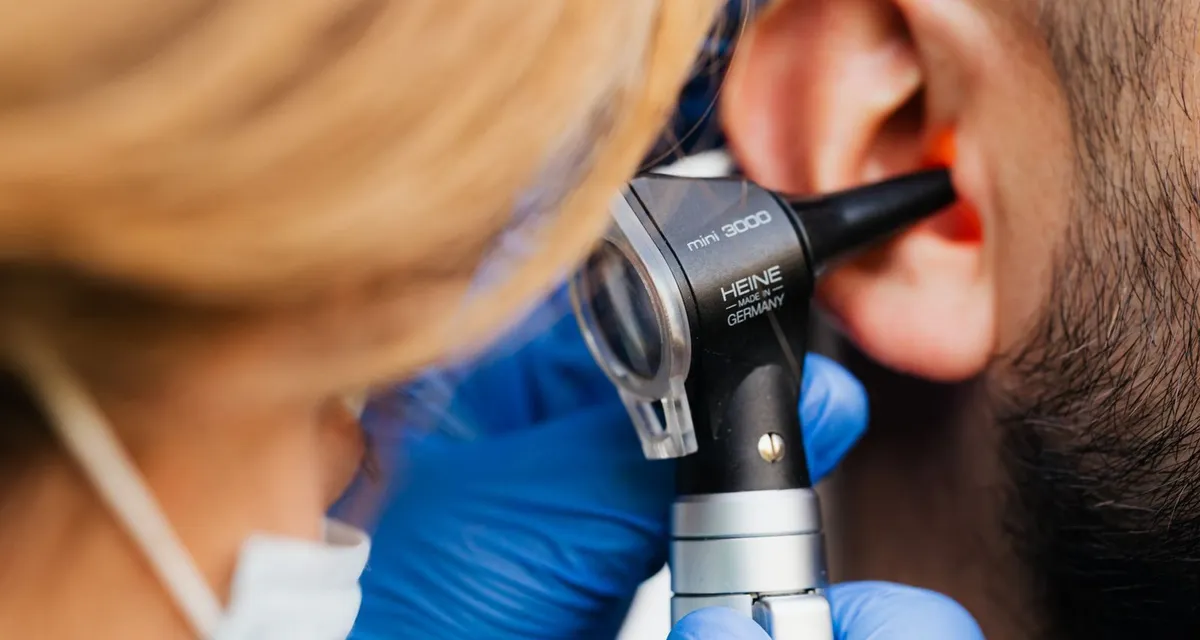
The two can be hard to tell apart from the outside. Pain when the outer ear is pulled or pressed points towards the canal, while dulled hearing with a blocked nose and a cold points inwards, but a clinician looking in the ear is the only reliable way to know.
What happens to the ear in flight
A commercial cabin is pressurised, but to the equivalent of roughly 6,000 to 8,000 feet rather than to sea level. This cabin altitude is reached during the climb and held through the cruise.
As the aircraft climbs and cabin pressure falls, air in the middle ear expands and usually escapes down the Eustachian tube without anyone noticing. Descent is the harder direction. Cabin pressure rises, and air has to travel back up a tube that may now be swollen shut. If it cannot, the eardrum is pulled inwards.
The result is ear barotrauma: pain, muffled hearing and a feeling of fullness that can last for days after landing. Most cases settle on their own. Occasionally the eardrum bruises or tears. Rarely the inner ear is affected, and new dizziness, spinning or a sudden drop in hearing after a flight should be assessed promptly rather than left to settle.
A perforated eardrum behaves differently. Because air can pass through the hole, pressure equalises across the drum, and flying can be more comfortable than people expect. Grommets work on the same principle. Ear surgery is a different matter, and published aeromedical guidance commonly attaches a waiting period after operations on the middle ear. That decision belongs to the surgeon.
What decides it, and what helps
The most useful test is simple. If you can make your ears pop by swallowing, or by gently blowing with your nose pinched and mouth closed, the tube is working. If you cannot, the descent is likely to hurt, and a GP or pharmacist may advise delaying if the trip can move. NHS advice is broadly the same: an active middle ear infection or heavy congestion is a reason to think twice about flying.
Airlines do not usually ask for a fit to fly certificate for an ear infection, and there is no airline rule that decides it for you. The judgement is clinical and it is yours to ask for.
If the flight has to go ahead, most of the effort belongs to the last half hour:
- Stay awake for the descent so you keep swallowing.
- Swallow, yawn or chew, and gently blow with the nose pinched if that clears the ears.
- Use a decongestant nasal spray if a pharmacist recommends one, timed as they direct before descent.
- Take pain relief before the descent starts, not once the pain has arrived.
For a baby or young child, a feed, a drink or a dummy during descent does the swallowing for them. Children are more prone to ear pain in flight because their tubes are narrower, and an active infection makes that worse.
What this means if you are managing a case
An ear infection is rarely the reason anybody is repatriated. It matters as a second problem in a patient being moved for something else.
The patients who cannot protect their own ears are the ones to plan for: a patient who is sedated, ventilated or too unwell to swallow on command, or one lying flat on a stretcher with a heavy cold. A medical escort can anticipate the descent and manage pain, but cannot open a blocked tube. Where the clinical picture justifies it, an air ambulance can be flown with a lower cabin altitude, at a cost in route, fuel and flight time that has to be weighed against the benefit.
None of this is complicated. It needs somebody to ask about the ears before departure rather than after landing. That is the discipline described in medical repatriation and patient transport, and the reasoning behind matching the transport to the patient is set out in what good repatriation actually looks like.